







Screen content conversations with children deserve a different question from “how many minutes?” A new Indonesian school study found an association between parent-reported content discussion and lower psychosocial-symptom scores. It did not test a conversation programme or show that talking prevents mental-health conditions in Nigerian children.
Featured image: AI-generated conceptual Nigerian parent-child conversation. The people are fictional and are not participants in the Indonesian study.
This evidence guide includes two original coefficient charts, a three-question discussion infographic and four free CSV tools. It separates the statistical finding from editorial conversation ideas and a private, unscored log. Research checked on 9 November 2026; no Nigerian family data were collected for this article.
What screen content conversations meant in this study
The BMC Psychology paper by Sanjaya and colleagues was published 4 November 2026. Data came from 147 children aged 6–13 at one public elementary school in Surabaya, Indonesia, during January–March 2026. Parents reported screen use, monitoring and symptoms. The publisher identifies the available paper as an accepted early-access version subject to further editing.
Active monitoring meant whether a parent reported discussing the content a child watched or played. Restrictive monitoring concerned coded rule categories, while co-viewing concerned shared viewing frequency. These are distinct measures. A family can watch together without discussing a scene, or discuss a game without having watched every minute together.
Read screen content conversations coefficients in score units
The selected adjusted coefficient for active monitoring was B−1.77, with a 95% confidence interval from−2.99 to−0.56. For screen use above two hours daily versus two hours or less, B was 1.90, with an interval from 0.60 to 3.19. These are differences in PSC-17 total-score points, not percentages or risk ratios.
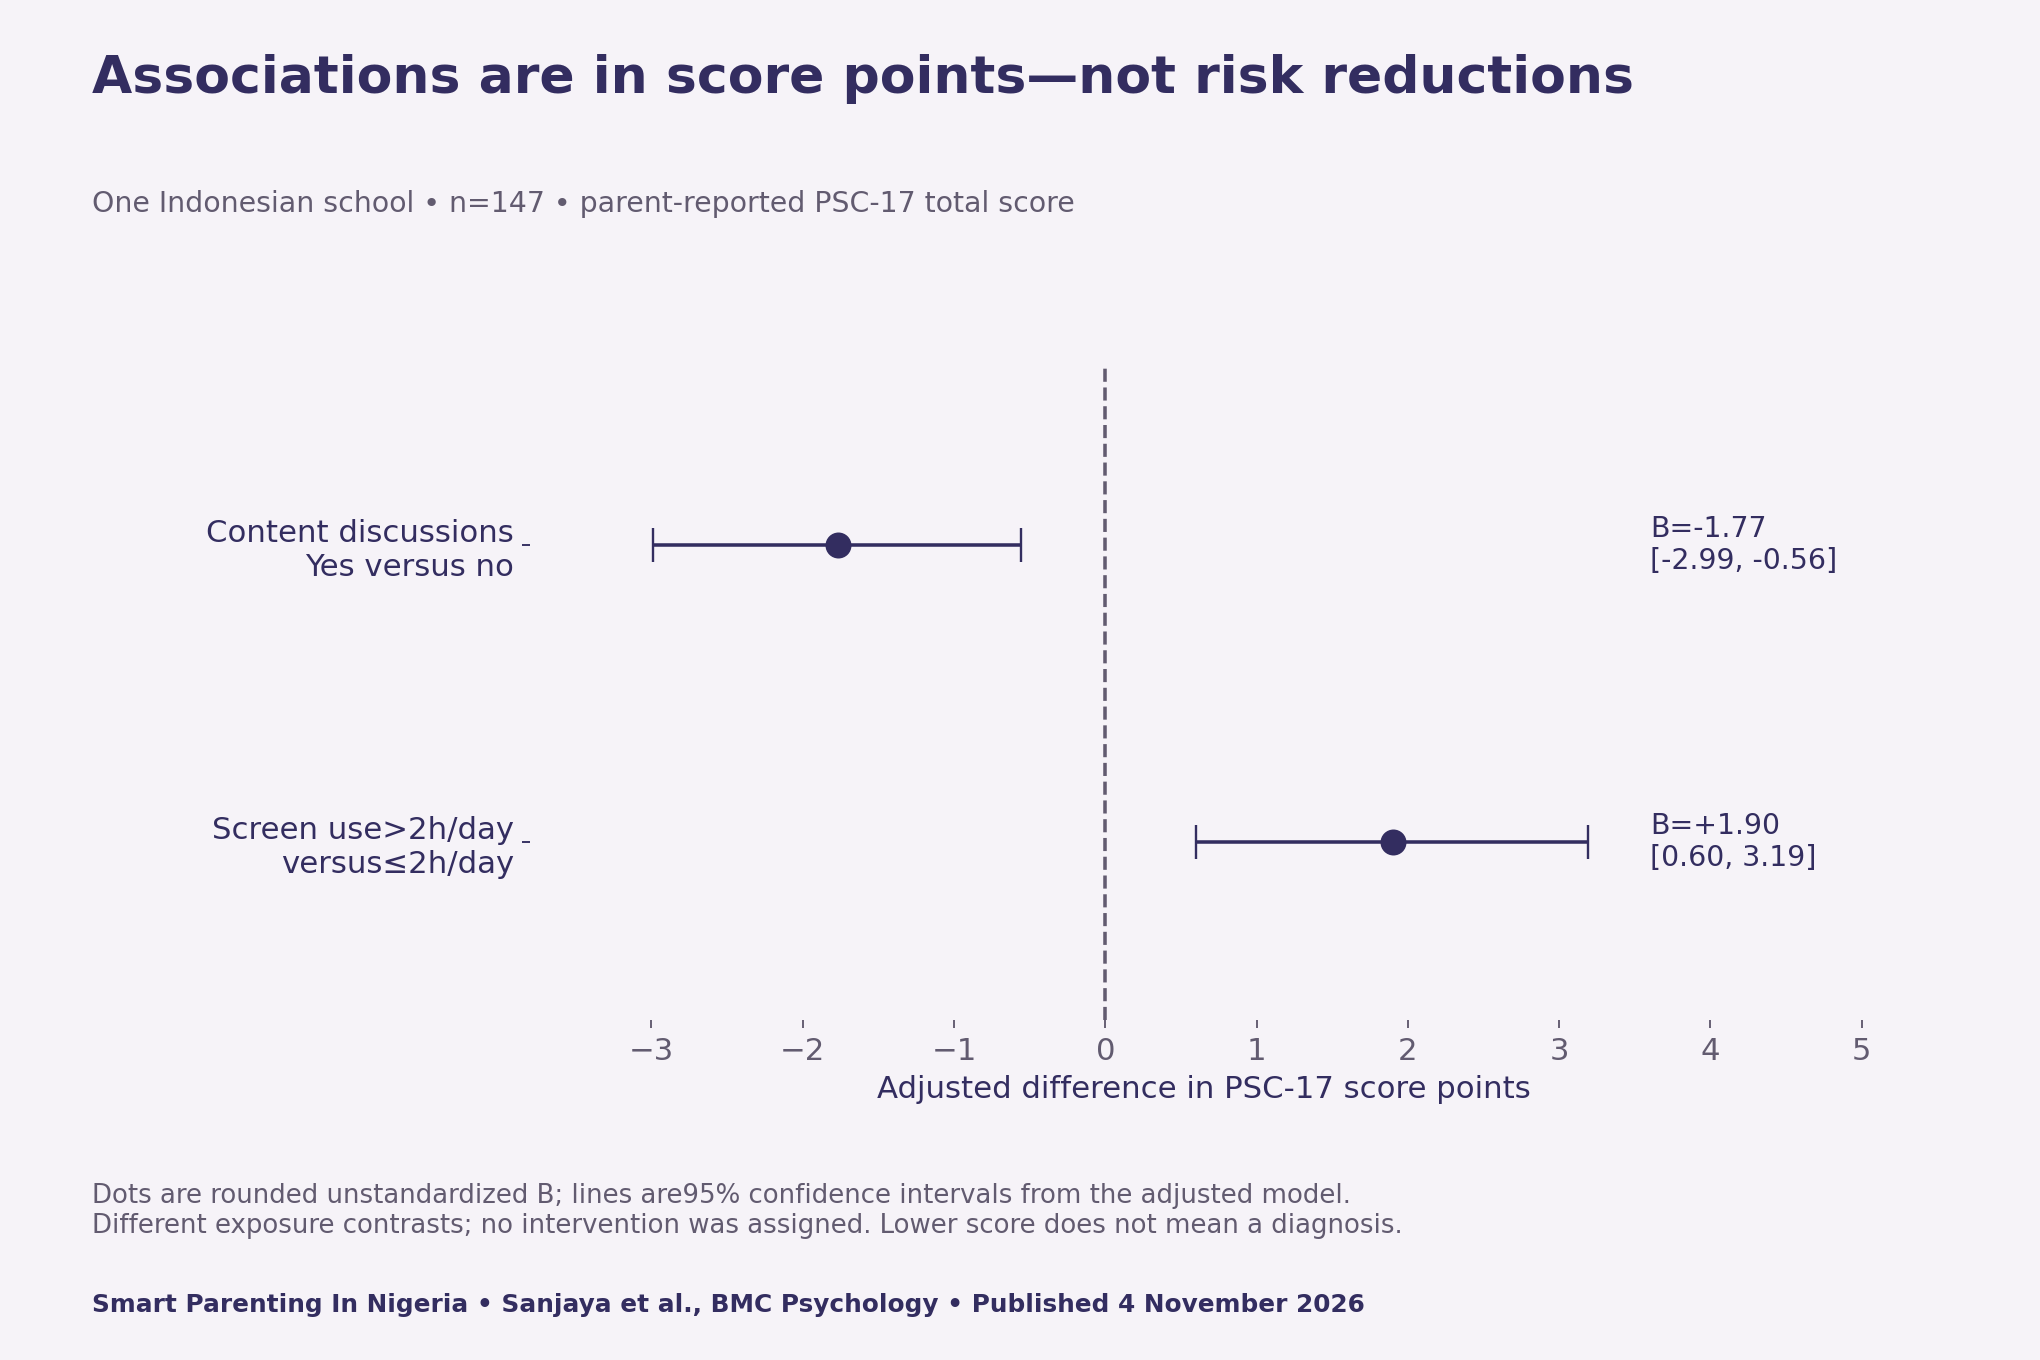
A negative coefficient describes a lower modelled score for that contrast after the source’s adjustments. It does not mean a child’s chance of a disorder fell by 1.77%, or that one conversation will remove 1.77 points. The study did not assign families to different approaches and observe a treatment response.
The zero line helps readers see where an interval lies relative to no modelled difference. However, an interval excluding zero does not settle whether the relationship is causal. Adjustment also cannot account for every unmeasured influence. Family routines, reporting and pre-existing difficulties may affect the observed relationship.
Why the sensitivity check matters
The accepted manuscript’s sensitivity section describes a 13-child subgroup whose parents reported unfollowed rules and rare co-viewing. Excluding that selected group changed the sample to 134, calculated as 147 minus 13. Active monitoring and screen time retained their selected associations, while restrictive monitoring and co-viewing no longer met the reported significance criterion in that check.
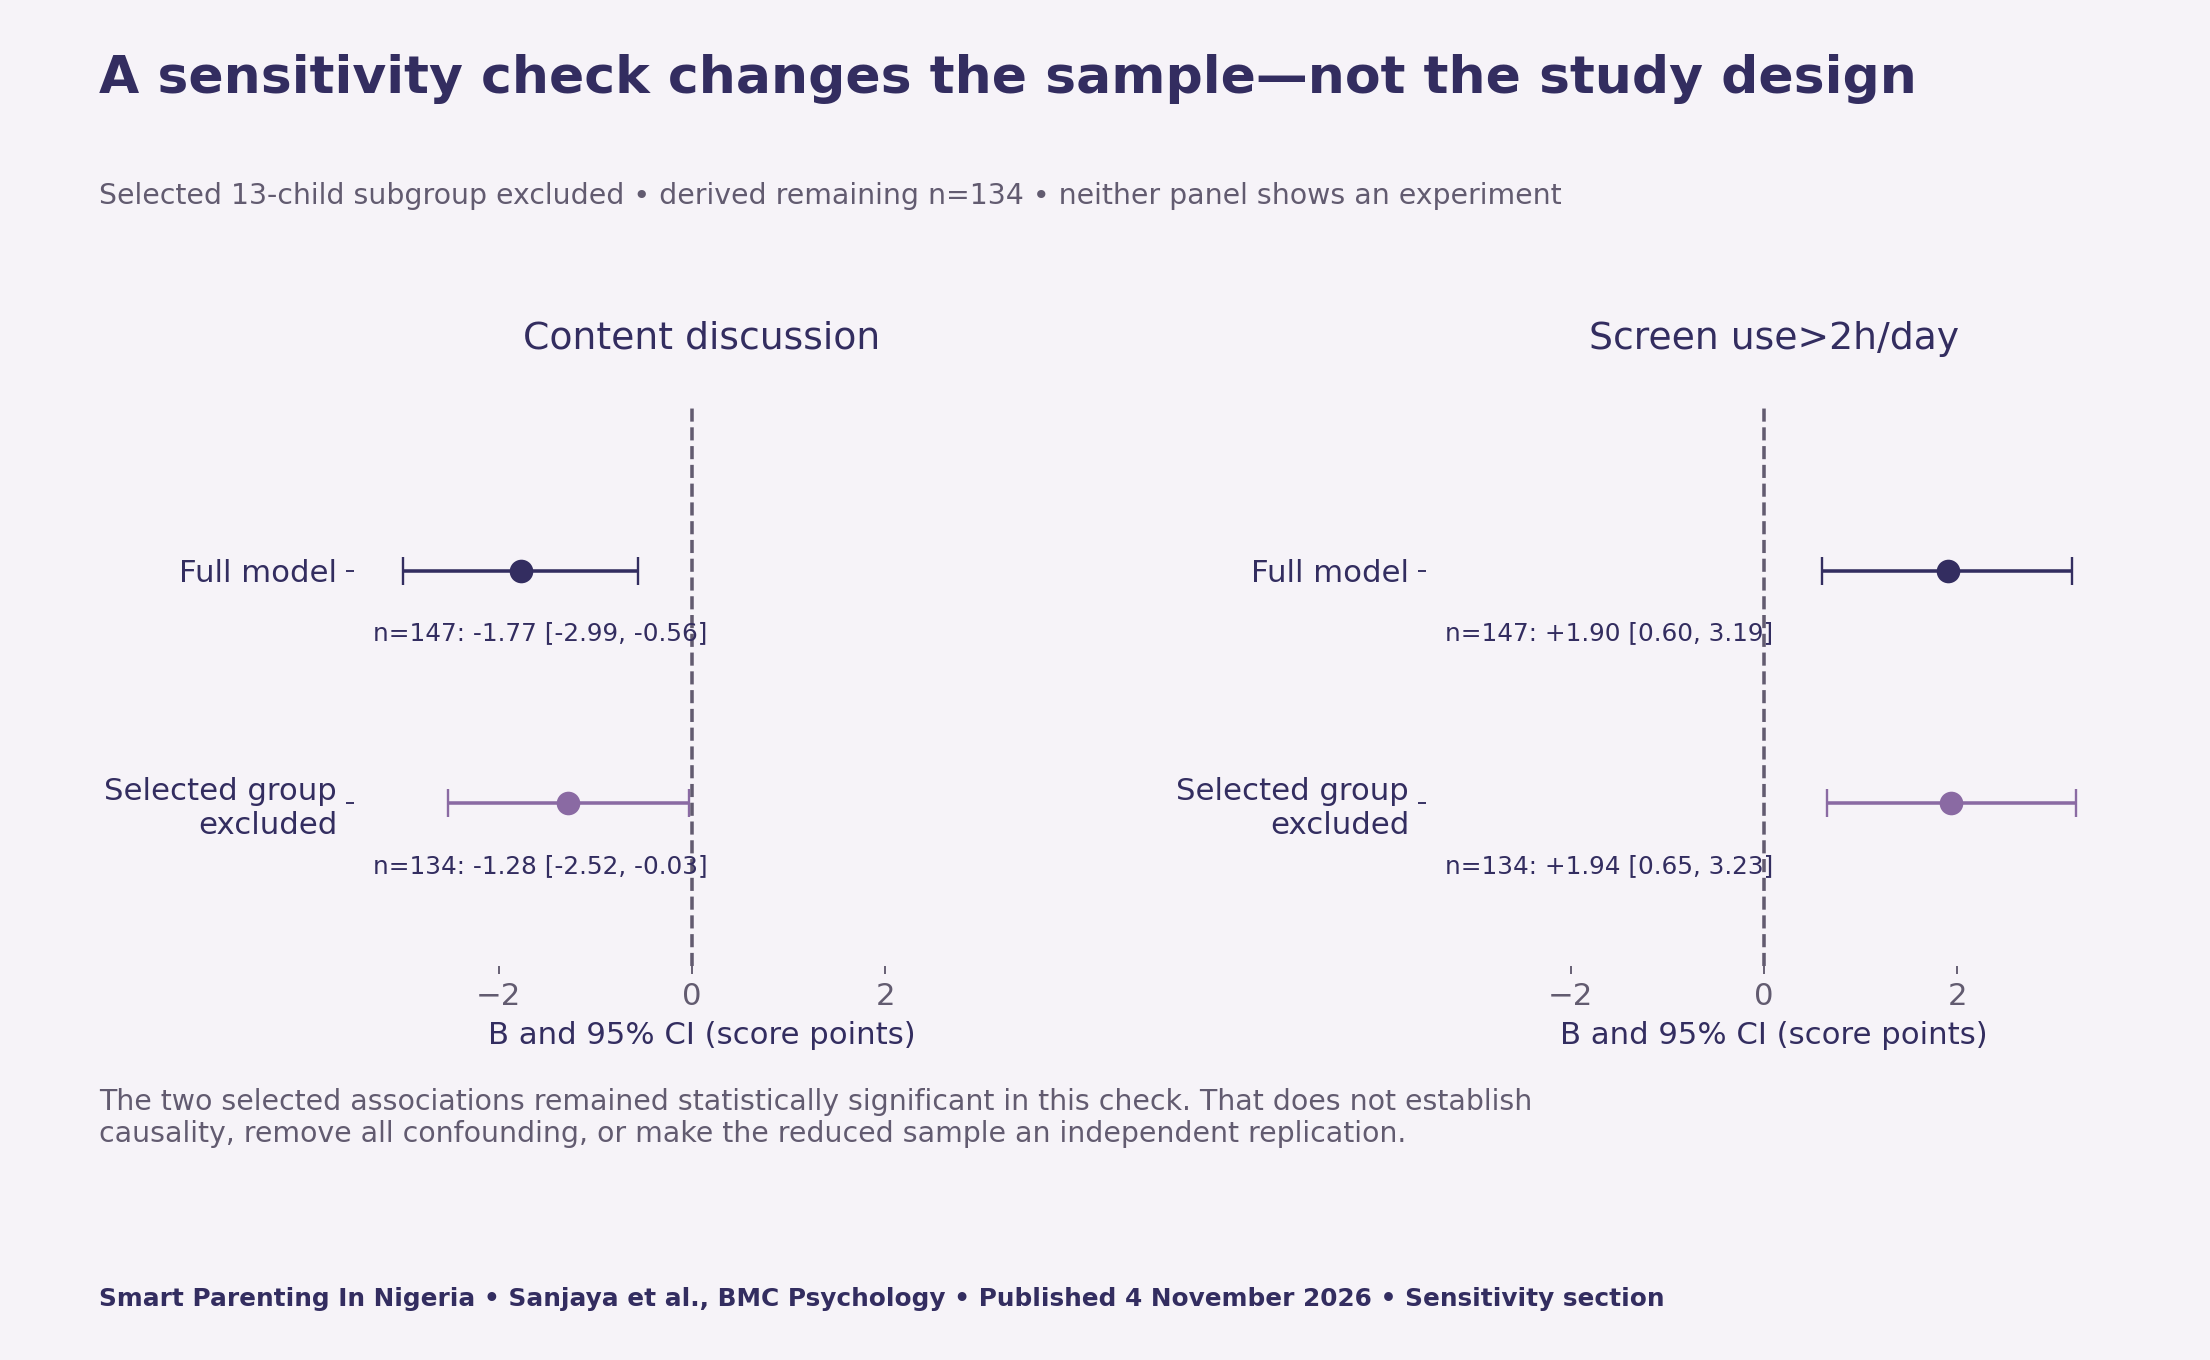
A sensitivity analysis asks how a result behaves under a different analytical choice. It is not a second school or a new trial. Nor does loss of significance prove that all rules or all shared viewing are ineffective. The useful lesson is to read the main result beside its robustness limits rather than promote a single model as a universal parenting rule.
A screening result is not a diagnosis
Seven children, reported as 4.8%, crossed the paper’s total-score screening threshold. That small subgroup is not an estimate of Nigerian childhood mental-health prevalence. A screening result signals possible need for assessment; it does not establish a diagnosed condition. We do not reproduce the questionnaire or provide a home symptom-scoring tool.
The study used one school and a common parent reporter for exposures and outcomes. Its timing cannot establish which came first. The full manuscript also discusses selection and validation limits. A finding that remained in several models is still bounded by that design and population.
Separate screen content conversations from rule enforcement
For a family discussion, start with what the child noticed about a particular story, game or claim. Then ask what they think it means. Keep a question about whether a household rule was followed in a separate column. Combining all three into one “good screen use” score would hide the distinction the article is trying to explain.

Examples might be “What made that character’s choice seem fair?”, “How could we check whether that claim is true?” or “Which part would you like me to explain?” These prompts are original editorial examples. Adapt language and communication format to the child; do not treat a particular answer as evidence of a disorder.
The site’s broader screen-time guide and digital-parenting overview cover wider household context. This report’s narrower purpose is to audit one study and distinguish the evidence from ideas for a conversation. It does not establish a universal causal two-hour threshold.
Parenting Made Just for You
Get personalized Parenting Solutions tailored to your child’s needs. Transform your parenting journey with expert guidance in 1-3 days.
Get StartedUse a private log without collecting identifiable child data
The blank log records a content item or theme, a question, the adult’s explanation and an agreed follow-up. It has no child-name, school, contact-detail or symptom-score fields. Keep any completed notes private. The downloadable file contains no participant records and does not send a family’s responses to this website.
A log can help someone remember an unanswered content question. It should not become a surveillance record, a parent-performance score or a substitute for a child’s own account. There is no validated frequency target or outcome prediction built into this template. Leave an entry blank when there is nothing useful to record.
Seek appropriate support for persistent concerns
A content discussion is not a mental-health assessment. The National Institute of Mental Health’s established parent guidance advises seeking professional help when concerns persist, cause distress or interfere with daily functioning. That is older clinical context, not a result of this school study.
For a Nigerian family, discuss persistent concerns with an appropriately qualified local health professional. Do not wait for a private screen log to prove that a child deserves help, and do not use a research coefficient to diagnose them. This article supplies no imported foreign emergency-service numbers or remote diagnosis.
Download the source table and private discussion tools
The selected-coefficient file preserves score units and reference contrasts. A separate file records the selected full and reduced-sample estimates. The monitoring dictionary distinguishes three strategies and their reported sensitivity status. The fourth download is a blank private conversation log. None is a prediction model or a treatment plan.
- Selected adjusted screen-content coefficients (CSV)
- Selected sensitivity-check coefficients (CSV)
- Monitoring measures and evidence-status dictionary (CSV)
- Blank private content-discussion log (CSV)
Methods, source version and citation
We checked the publisher’s early-access page and full accepted manuscript, using rounded reported unstandardized coefficients rather than copying the paper’s standardized-coefficient figure. The original charts retain score units and uncertainty. No participant-level dataset, model refit or Nigerian intervention is presented. The 13-child exclusion is a source sensitivity check, not our new experiment.
Suggested citation: Smart Parenting In Nigeria(9 November 2026), “Screen Content Conversations: What the Study Can Tell Parents.” Attribute study findings to Sanjaya and colleagues, BMC Psychology, DOI 10.1186/s 40359-026-05934-z, published 4 November 2026. Our charts and unscored discussion assets are original presentations of selected factual findings and editorial questions; no source figure or clinical questionnaire is reproduced.


